✦ AI drafts. A human always approves.

The operating system
for hospitals, from India.

One system for a 30–100 bed hospital — OPD, wards, theatre, casualty, pharmacy, lab, billing and claims — with a dedicated database per hospital, AI that drafts every one of them while a named human always approves, and nothing sent without a signature. Built first for India's own complexity — ABDM-native, works when the internet doesn't, and it speaks Telugu — because software proven there travels anywhere.

No signup, no sales call. Pick a role and walk a real shift at a 60-bed hospital.
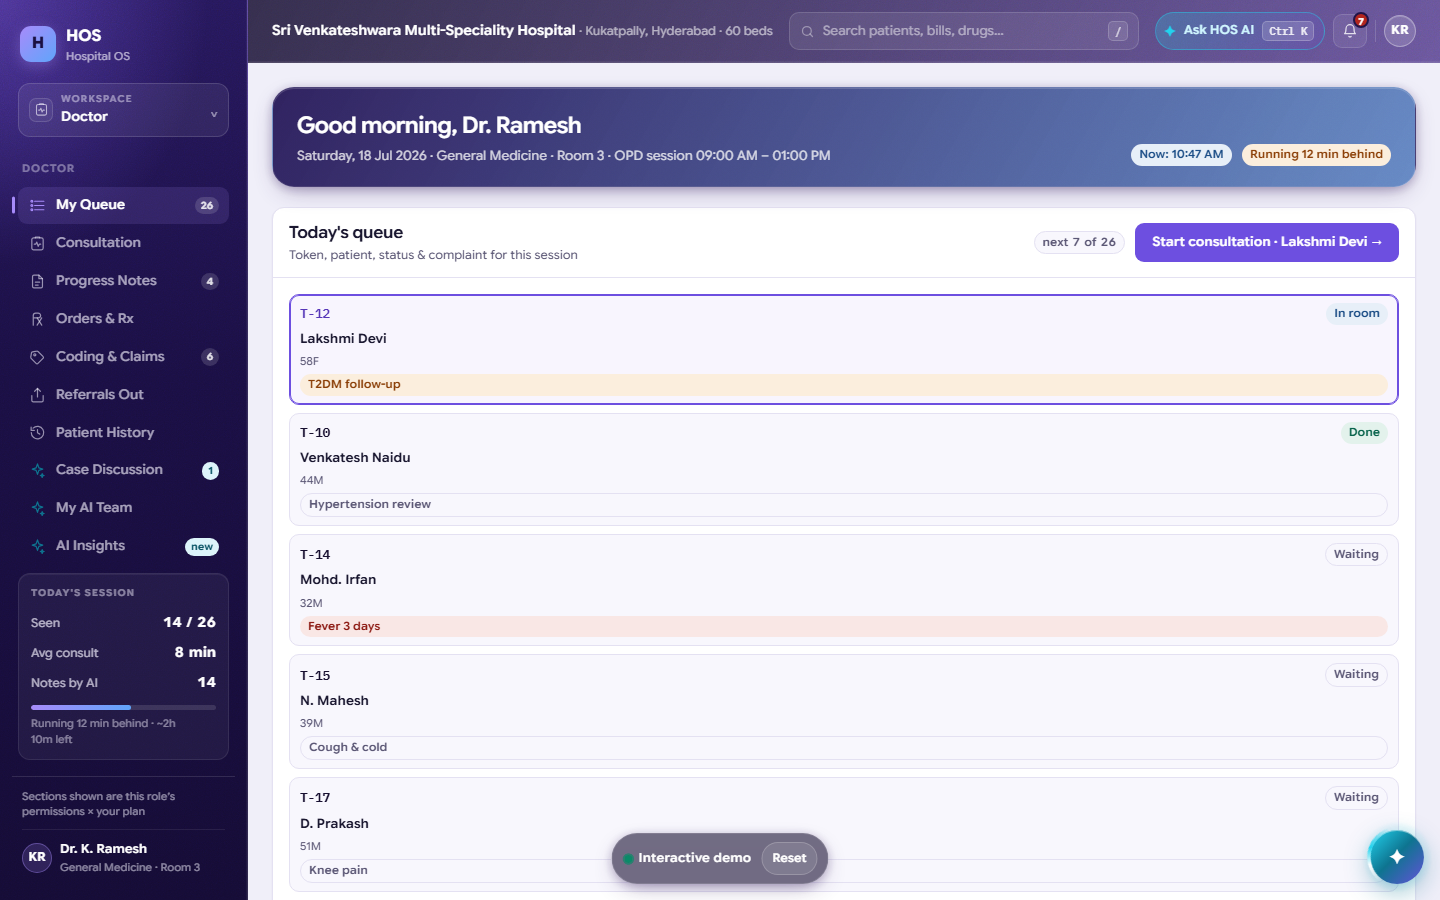
doctor workspace · 10:47 AM
The HOS doctor workspace: today's OPD queue of 26 patients with tokens, complaints and status, alongside session stats.
2–3 weeks
to go live — not a six-month rollout
16
workspaces, every one with AI built in
Your own DB
a dedicated database per hospital, never a shared table
100%
of AI actions signed off by a named human
The problem

Your hospital already runs on software.
It runs on paper, WhatsApp, and one person who knows everything.

A 60-bed hospital loses money where nobody can see it — charges that were charted but never billed, claims that missed their filing window, follow-ups nobody called. HOS closes those gaps because it is the same system the clinical work happens in.

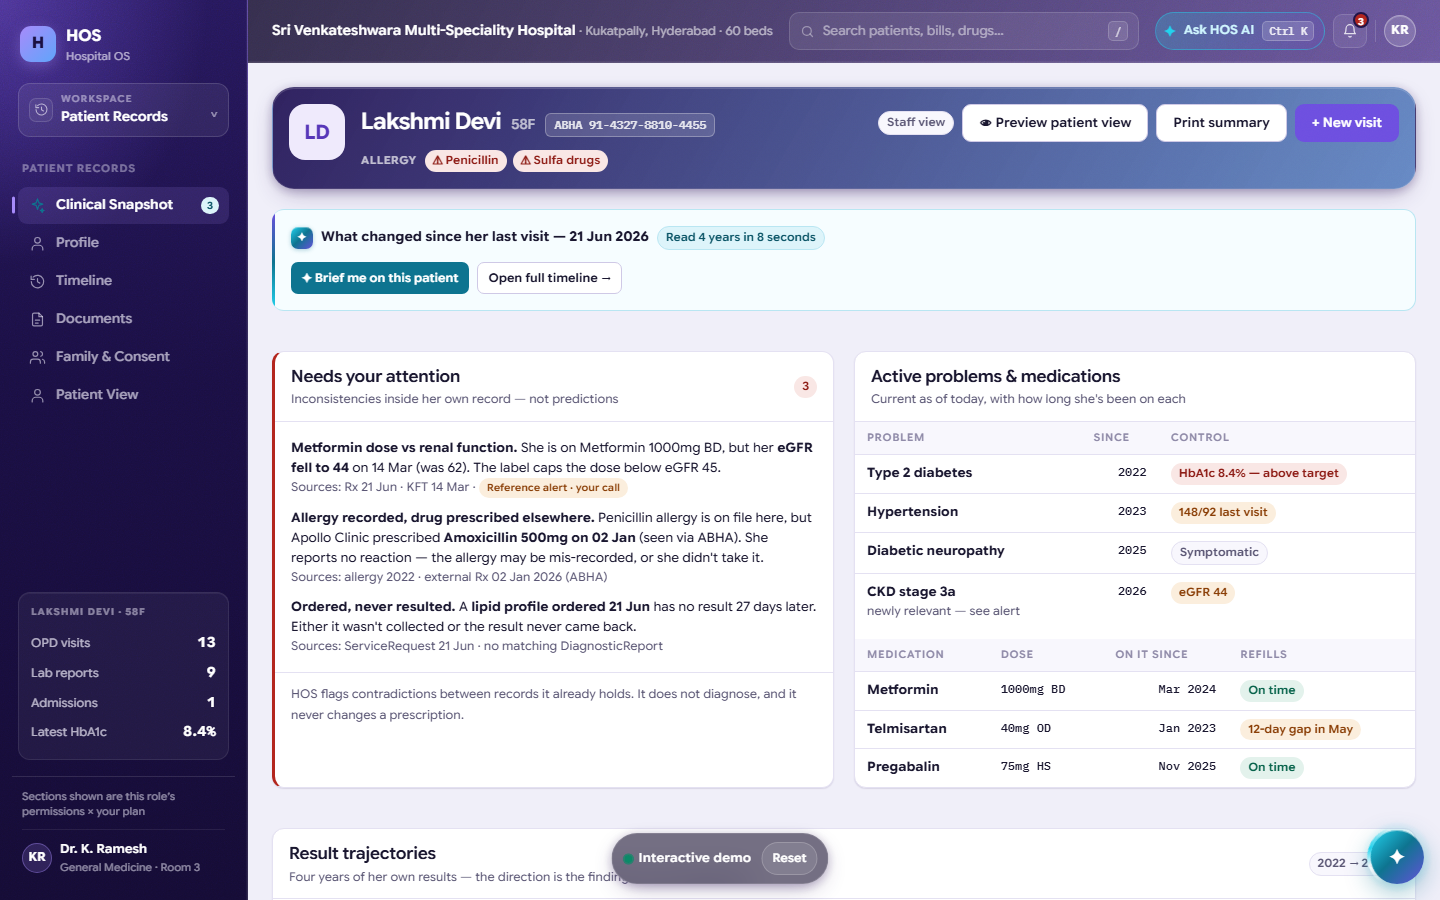
Clinical snapshot: what changed since the last visit, three record contradictions, and four years of result trajectories.

Four years of history, read before the patient sits down.

An Indian OPD consult is two to five minutes. It cannot start with reading a timeline. One screen says what changed, what contradicts, what's overdue — every claim linked to the record it came from.

→Metformin 1000mg BD flagged against an eGFR of 44 pulled from another hospital via ABHA
→A lipid profile ordered 27 days ago that never produced a result
→Retinal screening never done in four years of diabetes
Open patient records →
Claims and pre-auth: PM-JAY three-day clocks, IRDAI three-hour cashless clock, and a denial-appeal draft.

The claim clocks are the interface, not a detail.

PM-JAY gives you three days from discharge. IRDAI gives the insurer one hour to decide a cashless pre-authorisation, and three hours for final authorisation at discharge — two clocks on two different events, which is exactly why hospitals chase the wrong one. Miss a filing window and the hospital is non-compliant, not merely late — so the clocks sit at the top of the screen, each labelled with the event it actually runs from.

→Pre-auth assembled from the record — all 7 documents, so an incomplete request can't restart the clock
→Of 9 denials this month, 7 contradict the chart — appeals drafted with the evidence quoted
→And it says which 2 it won't appeal, because they're correct
Open billing & claims →
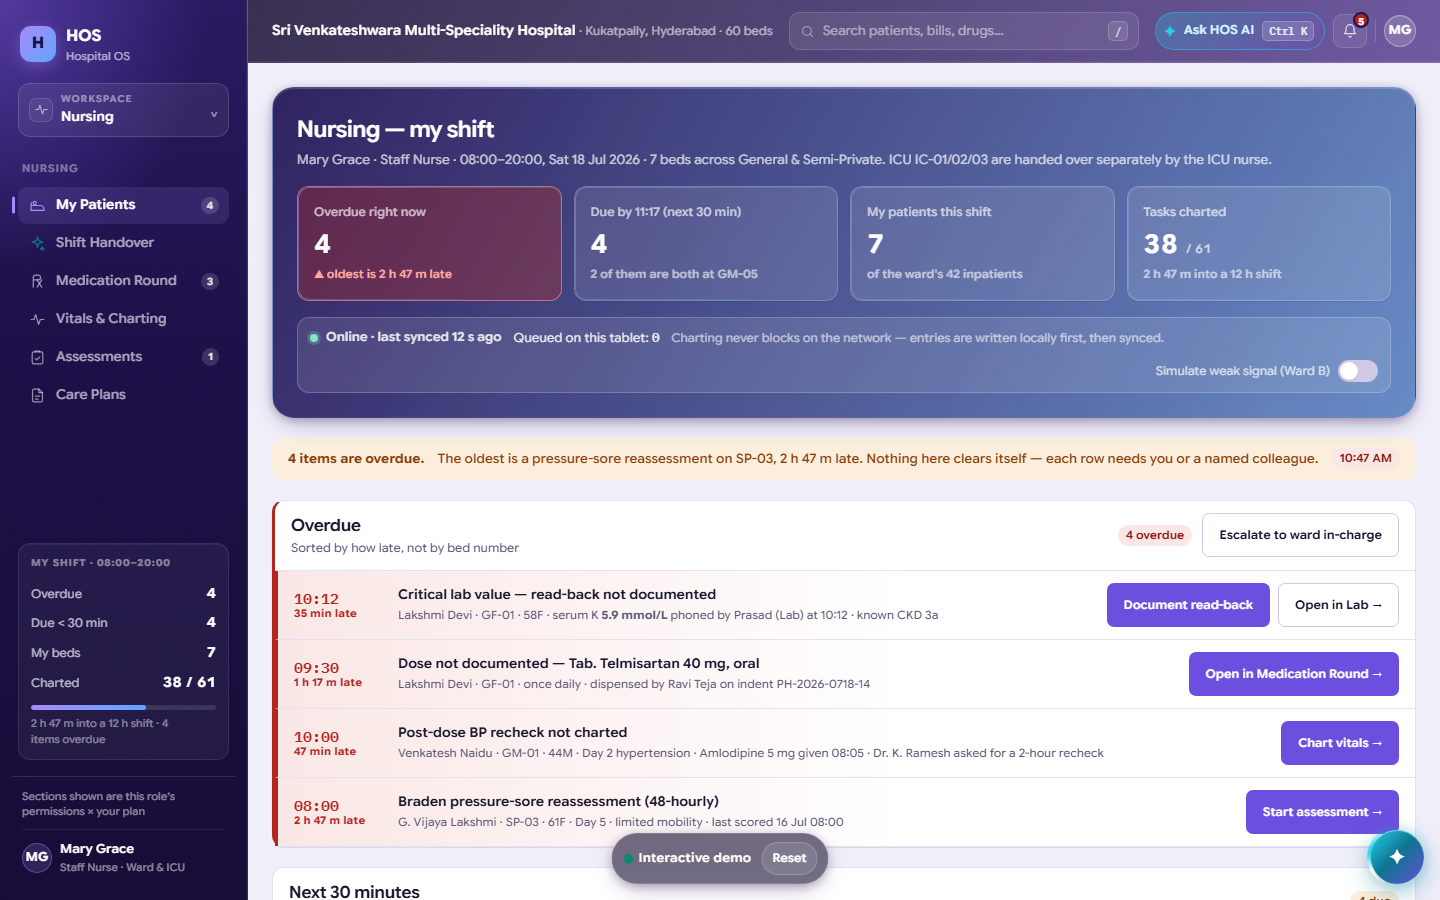
Nursing workspace: overdue tasks first, medication round with barcode verification, offline write queue.

Built for the person who lives in it for twelve hours.

A doctor uses HOS for minutes per patient. A ward nurse uses it for a whole shift, on a low-end tablet, in a corridor with no wifi. If nursing is painful the hospital never really adopts the system — so nursing got its own workspace.

→Barcode eMAR that blocks a wrong-patient scan — right drug, wrong bed, four of five rights matching
→SBAR handover drafted from the shift's own recorded events — but the recommendation stays human-written
→Writes queue on the device and drain when signal returns. Nothing lost, nothing charted twice.
Open the nursing shift →
Where we draw the line

AI that does the paperwork,
not the diagnosis.

Fewer than half of surveyed Indian doctors believe AI helps with diagnosis and treatment — and they're right to be careful. Under India's CDSCO framework, software that predicts, screens, diagnoses or recommends a treatment is a medical device and needs a licence. So we publish which side of that line every feature sits on, inside the product, where your compliance officer can read it.

✓Ships today. Consultation notes, discharge and operation notes, referral letters, ICD coding, claim assembly, denial appeals, stock forecasting, appointment calls.
✓Ships with a human decisive. Drug-interaction and allergy alerts, contradiction checks against the record, early-warning scores computed from vitals your nurses charted.
✕Switched off until licensed. Deterioration forecasting, diagnostic imaging AI, and triage that assigns clinical acuity. No hidden beta, no "clinical decision support" euphemism.
✓And you audit us. Per-worker accuracy, edit distance, drift alerts, and a hash-chained log — so you can prove to an assessor that nothing in your history was altered.
One system

Sixteen workspaces. Each one loads from the signed-in person's permissions.

A ward nurse never sees the tariff master. The owner sees everything. A patient signs into a different app entirely and can never reach a staff screen.

Every module

The whole hospital, sixteen screens.

From the front desk to the control plane — every workspace shipped, every one a real screenshot, not a mockup of a mockup.

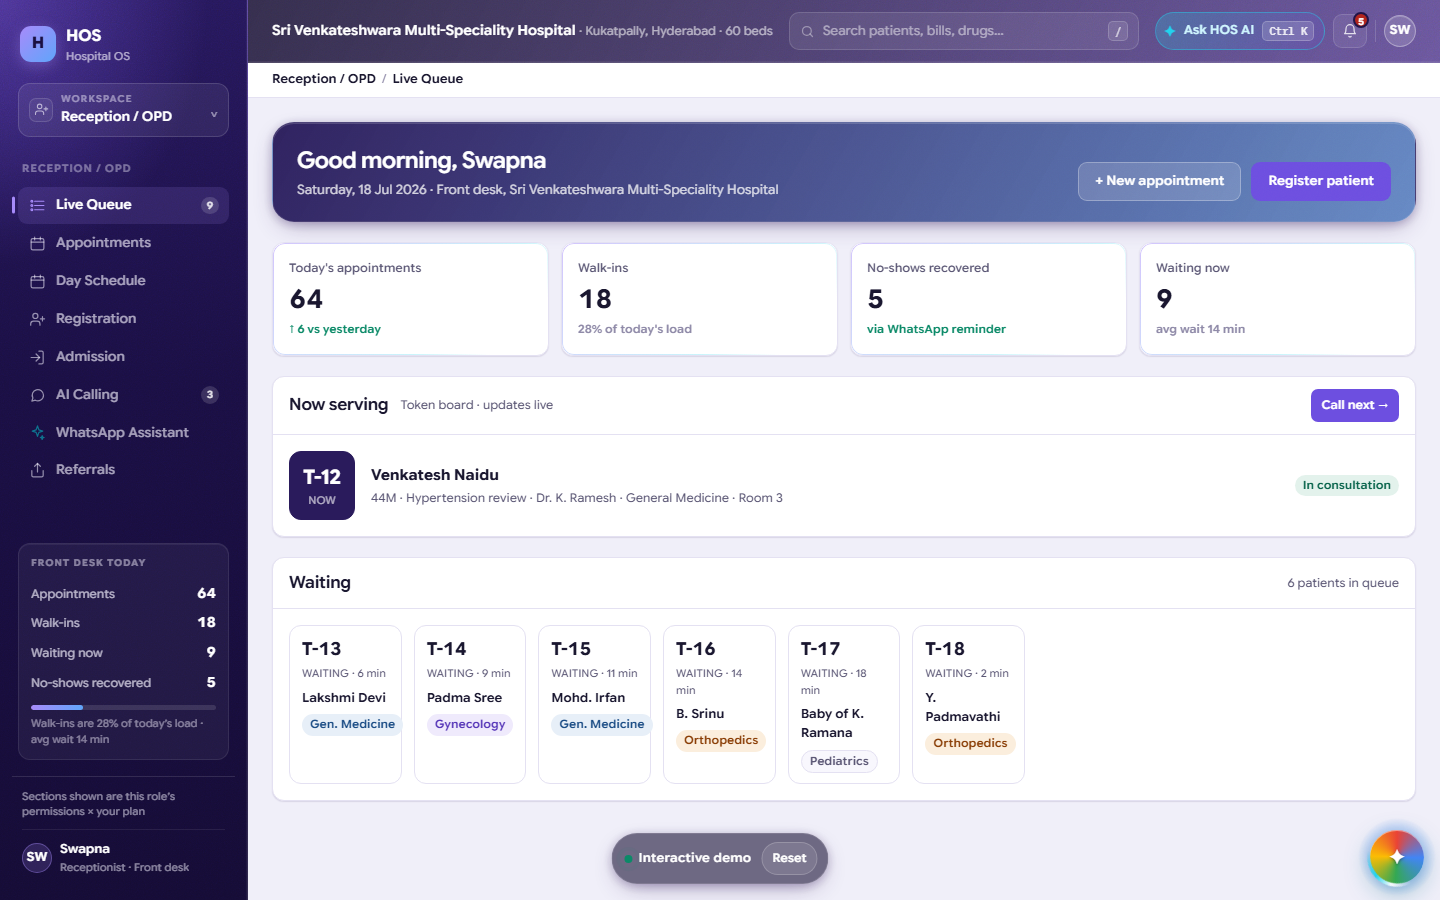
Reception and OPD live queue with today's appointments, walk-ins and now-serving token board.
01
Reception / OPD
Today's appointments, walk-ins, no-shows recovered, and who's waiting now — with a live token board.
Doctor workspace with OPD queue, tokens, and specialty AI agents for clinical discussion.
02
Doctor
The OPD queue, plus personalised and specialty AI agents for Socratic discussion — it asks, it never diagnoses.
Patient record with what changed, record contradictions, and multi-year result trends.
03
Patient Records
What changed since the last visit, contradictions across the record, and years of trends surfaced automatically.
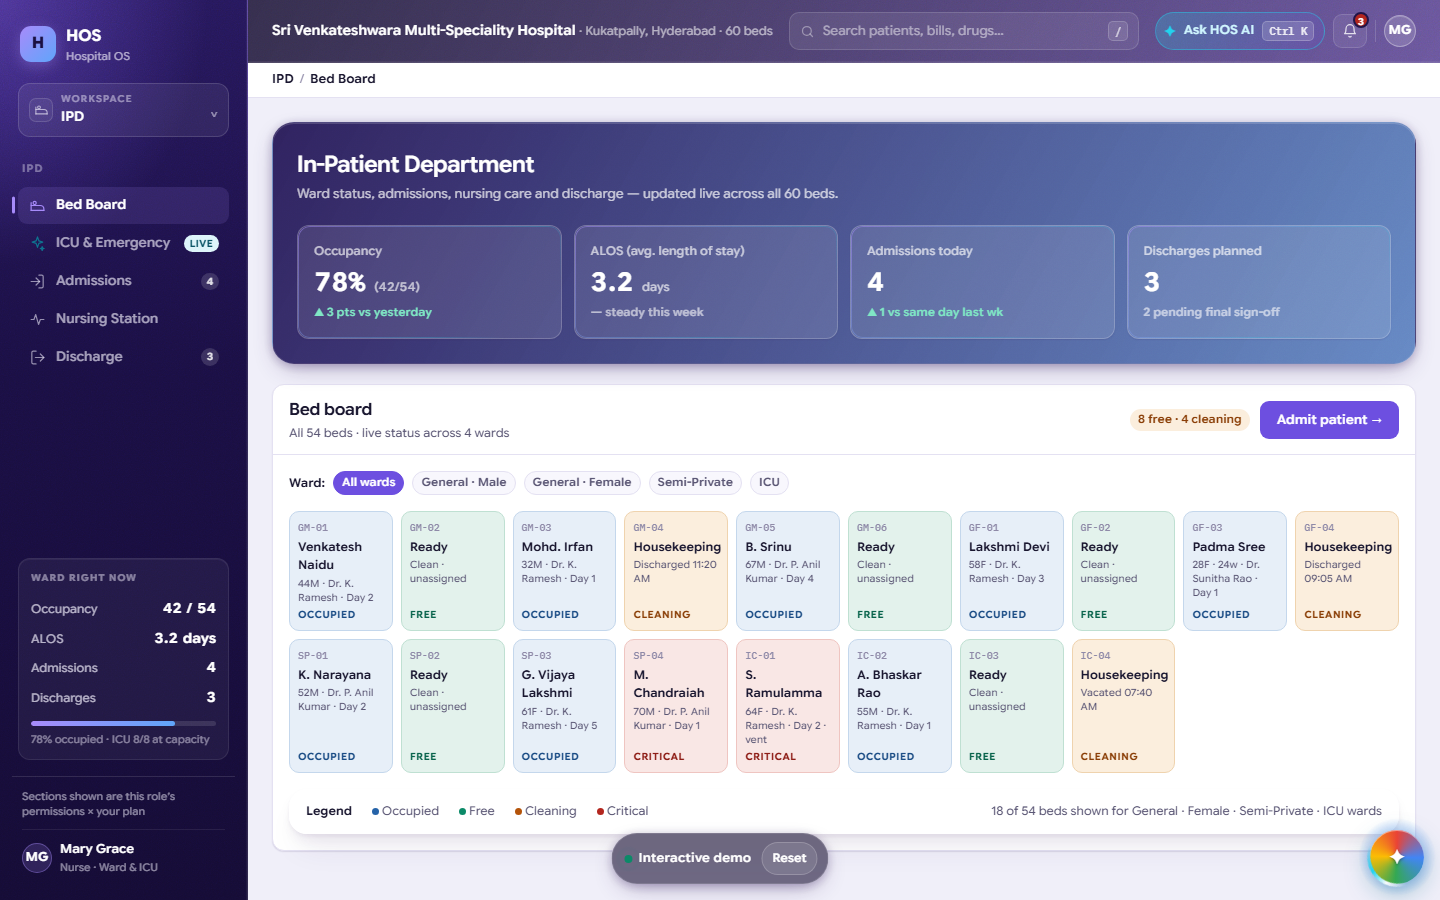
IPD bed board with live occupancy, ALOS, admissions and discharges across every ward.
04
IPD / Bed Board
Live occupancy, ALOS, admissions and discharges, with a colour-coded bed board across every ward.
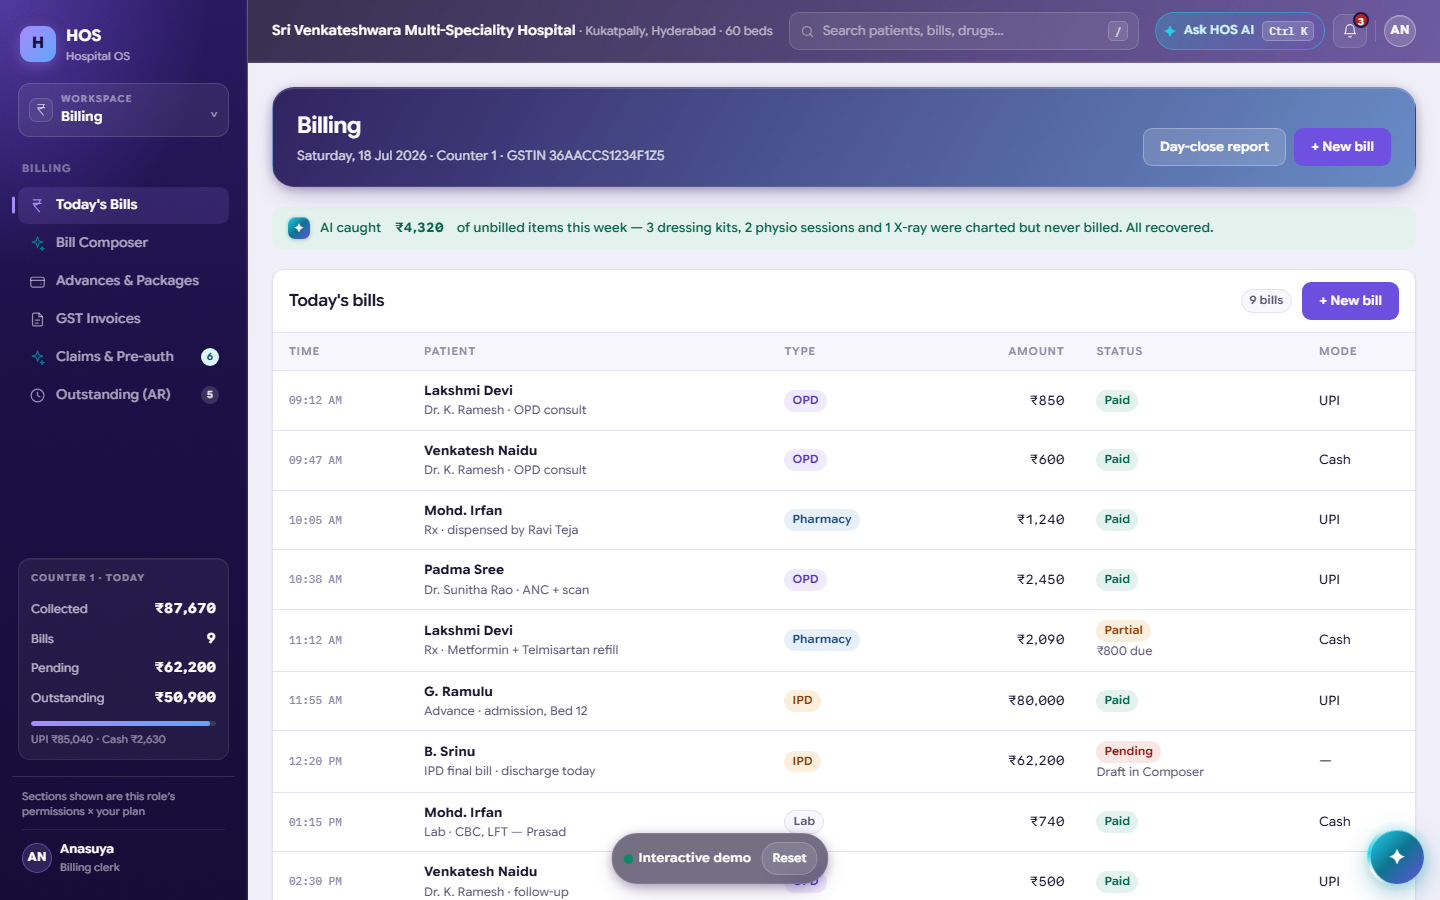
Billing and claims workspace with PM-JAY and IRDAI clocks and denial appeal drafts.
05
Billing & Claims
PM-JAY's 3-day filing window and IRDAI's 1-hour pre-auth and 3-hour discharge clocks as first-class UI, pre-auth assembly, and evidence-quoted denial appeals.
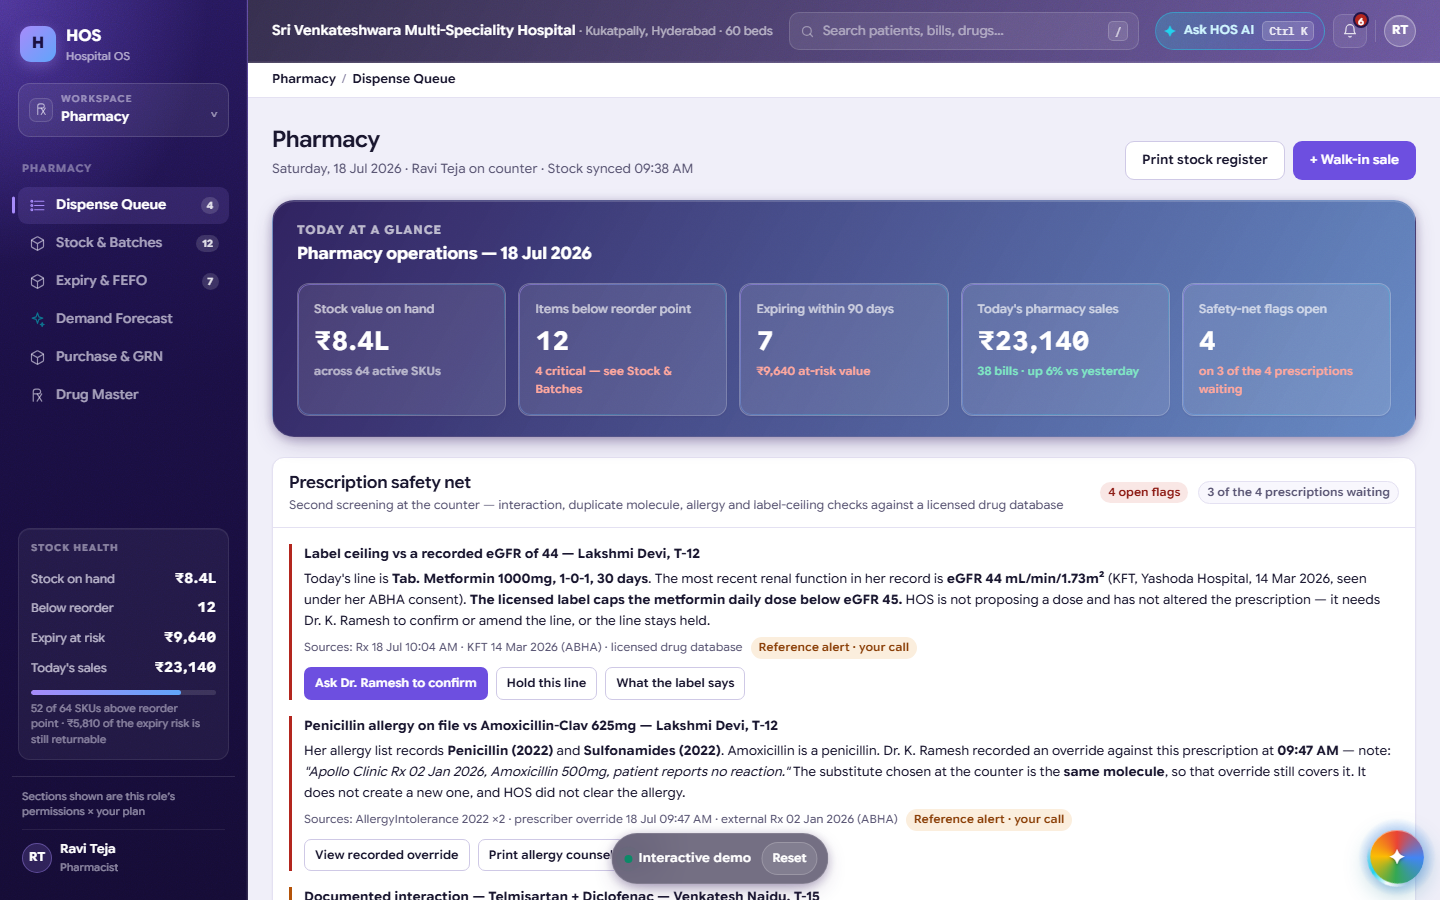
Pharmacy safety net with dose-vs-renal-function checks, allergy cross-checks and interaction flags.
06
Pharmacy
A second safety-net screening at the counter — dose ceilings, allergy and interaction checks. Reference alerts; the pharmacist decides.
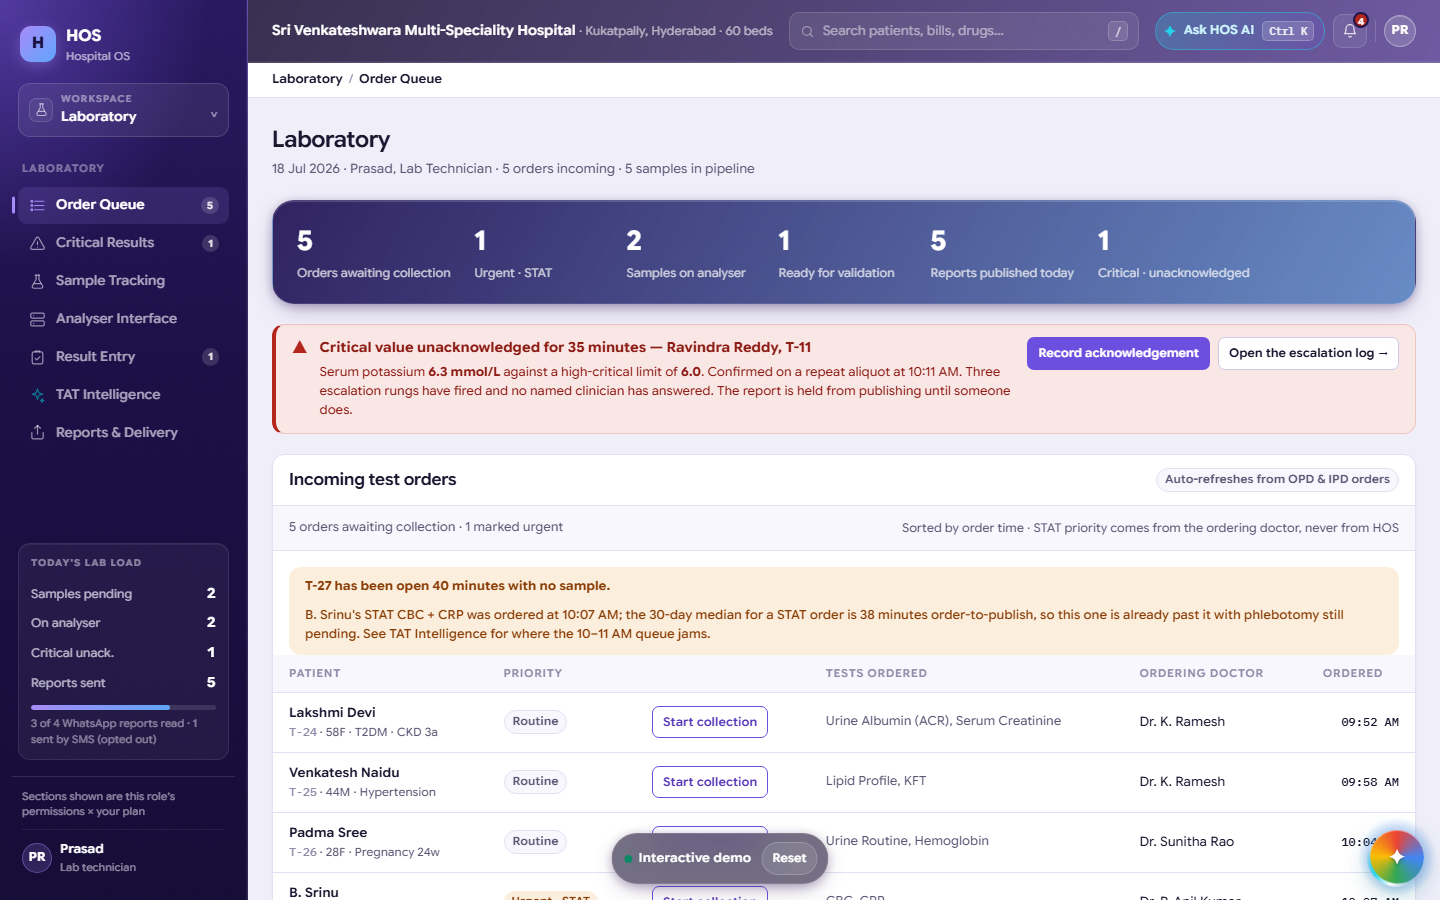
Laboratory order queue with critical value escalation and turnaround-time intelligence.
07
Laboratory
Order queue and critical-value escalation that holds a report until a named clinician acknowledges it.
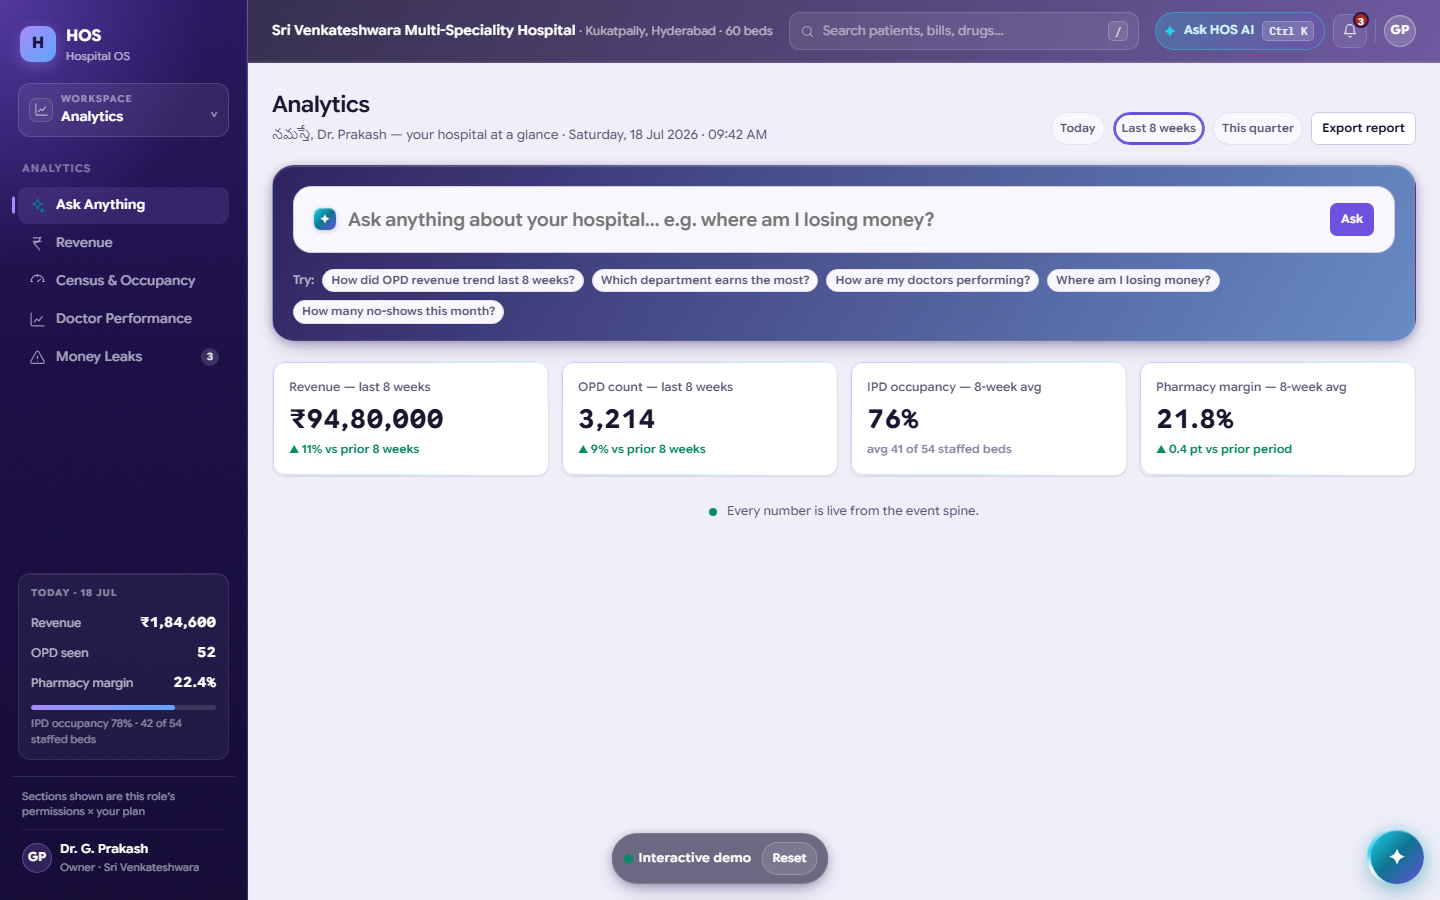
Analytics workspace answering plain-language questions with revenue and performance data.
08
Analytics
Ask a plain-language question, get revenue trends, department performance and money leaks — from live data.
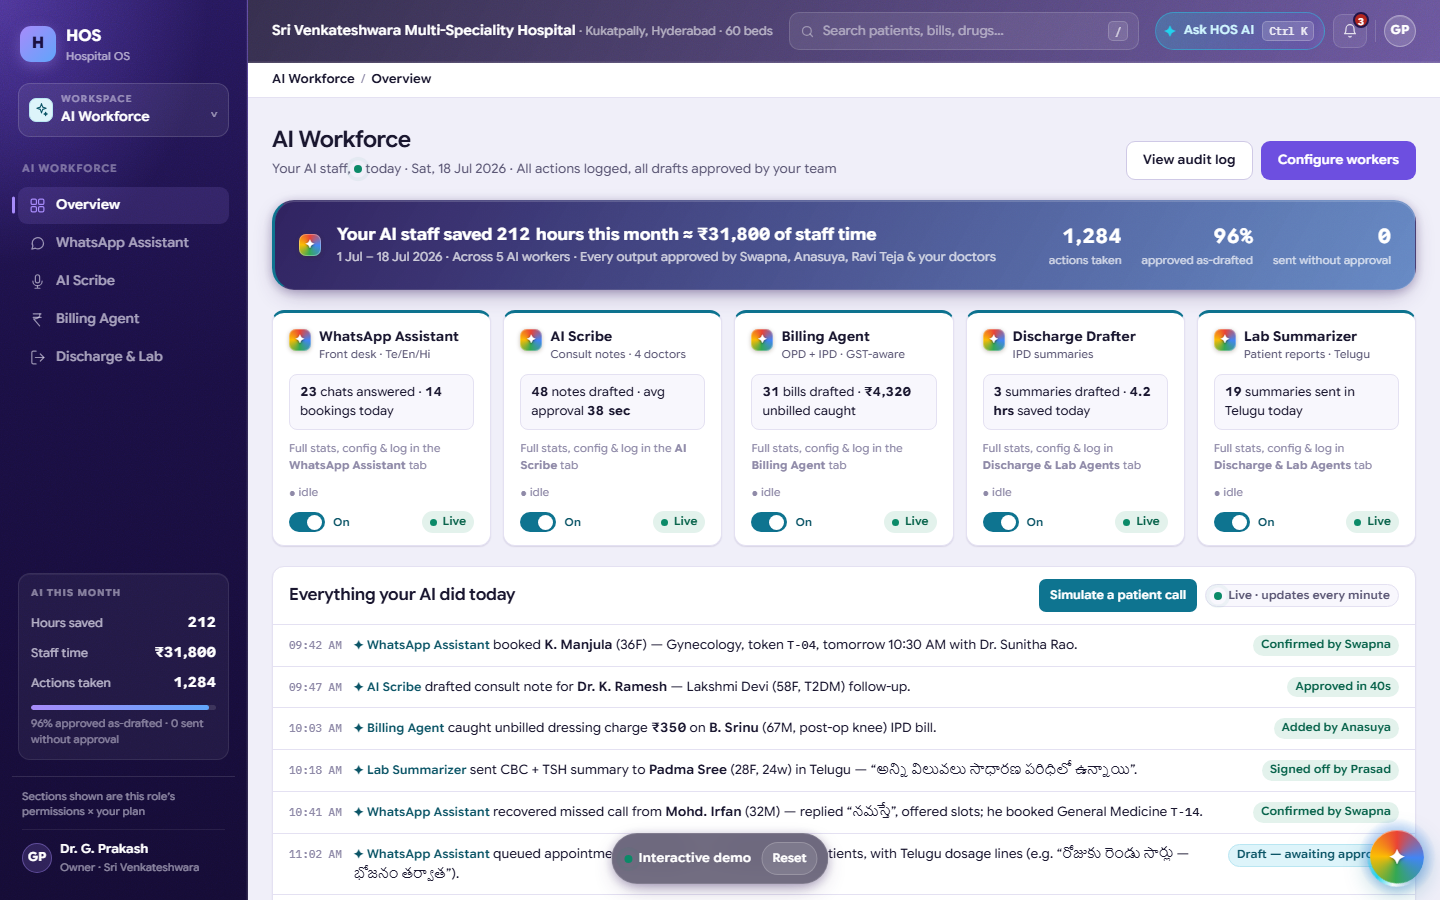
AI Workforce feed showing every AI worker's actions today with named human sign-off.
09
AI Workforce
Every AI worker's output today in one feed — hours saved, actions taken, and the named human who signed off each one.
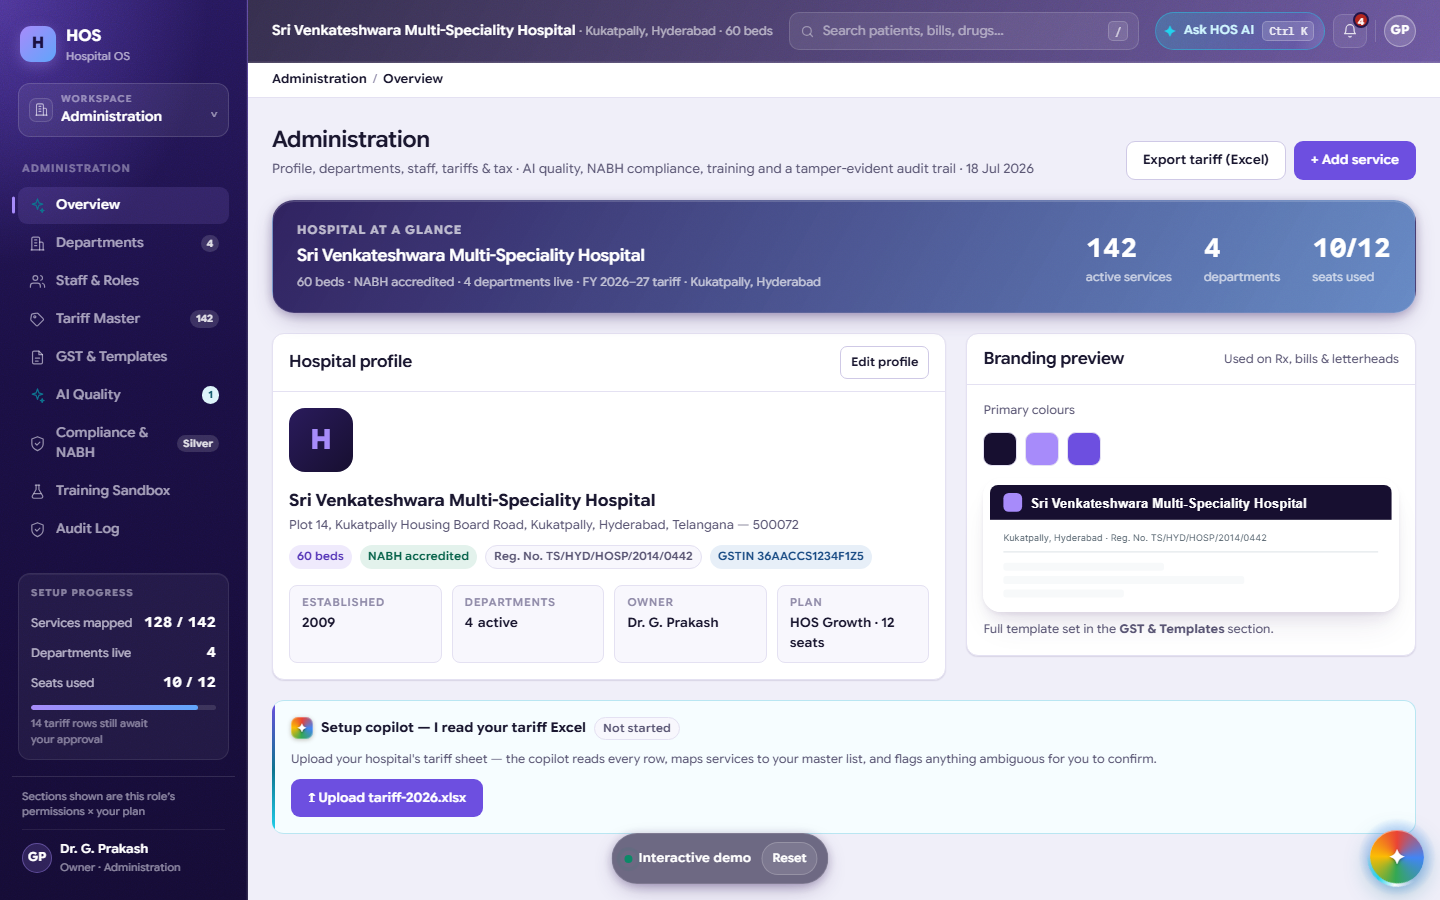
Administration workspace with hospital profile, tariff, NABH compliance and audit log.
10
Administration
Hospital profile, tariff and GST templates, staff, NABH compliance tracking, and a tamper-evident audit log.
Control plane fleet view across many hospitals with AI fleet kill switch and unit economics.
11
Control Plane
One person, many hospitals: an AI kill switch with mandatory reason capture, staged rollouts, per-tenant economics.
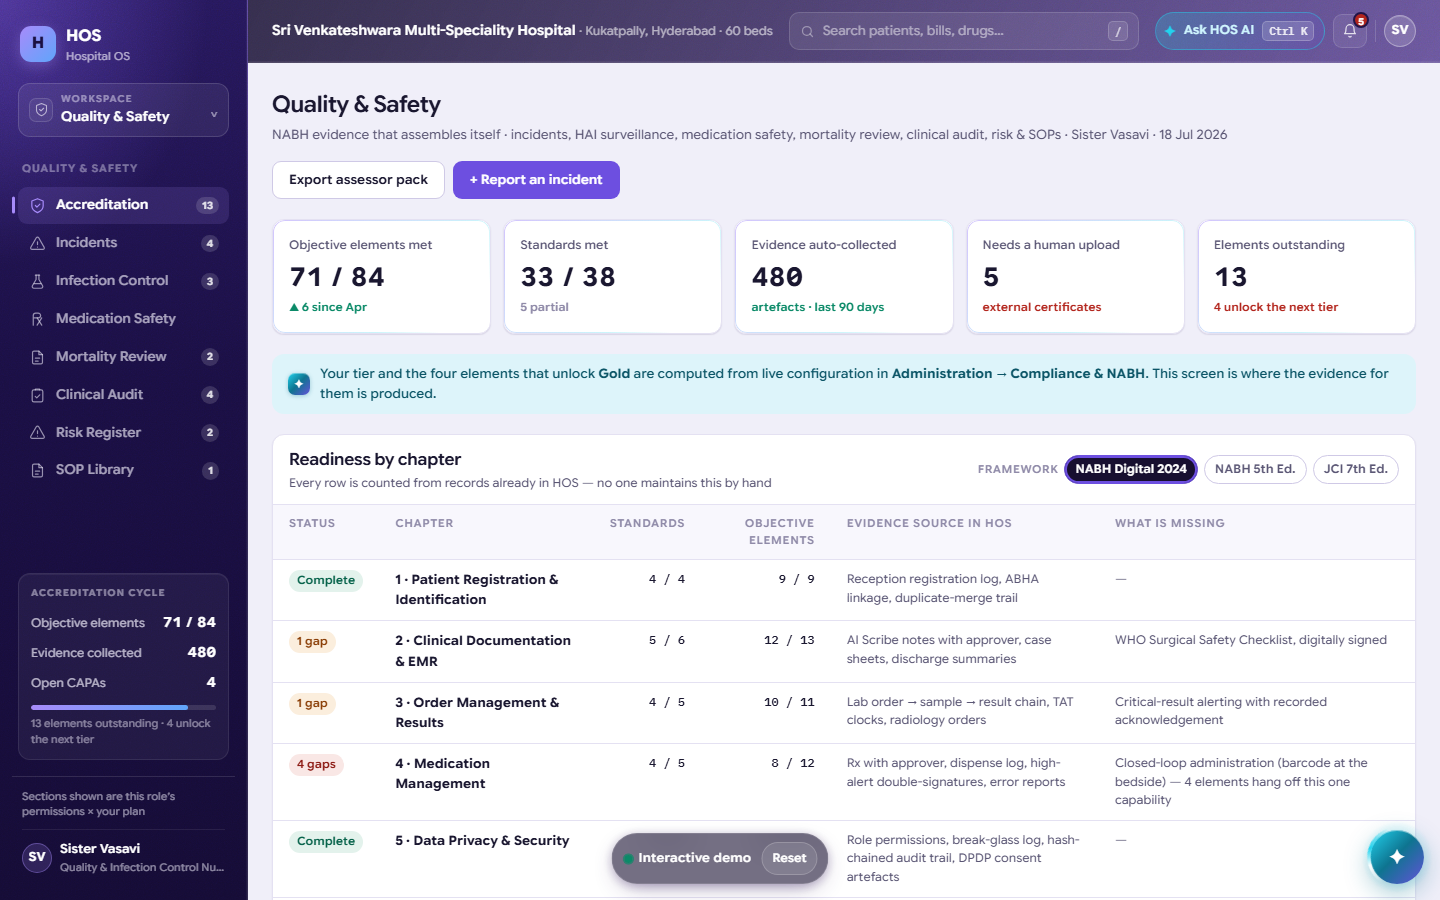
Quality and safety workspace with NABH accreditation evidence and incident reporting.
12
Quality & Safety
NABH accreditation evidence and incident reporting that assemble as a by-product of the work, not a paper project.
Nursing workspace with overdue tasks, barcode-verified medication rounds and offline write queue.
13
Nursing
Overdue tasks surfaced first, barcode-verified medication rounds, and an offline write queue for wards with no signal.
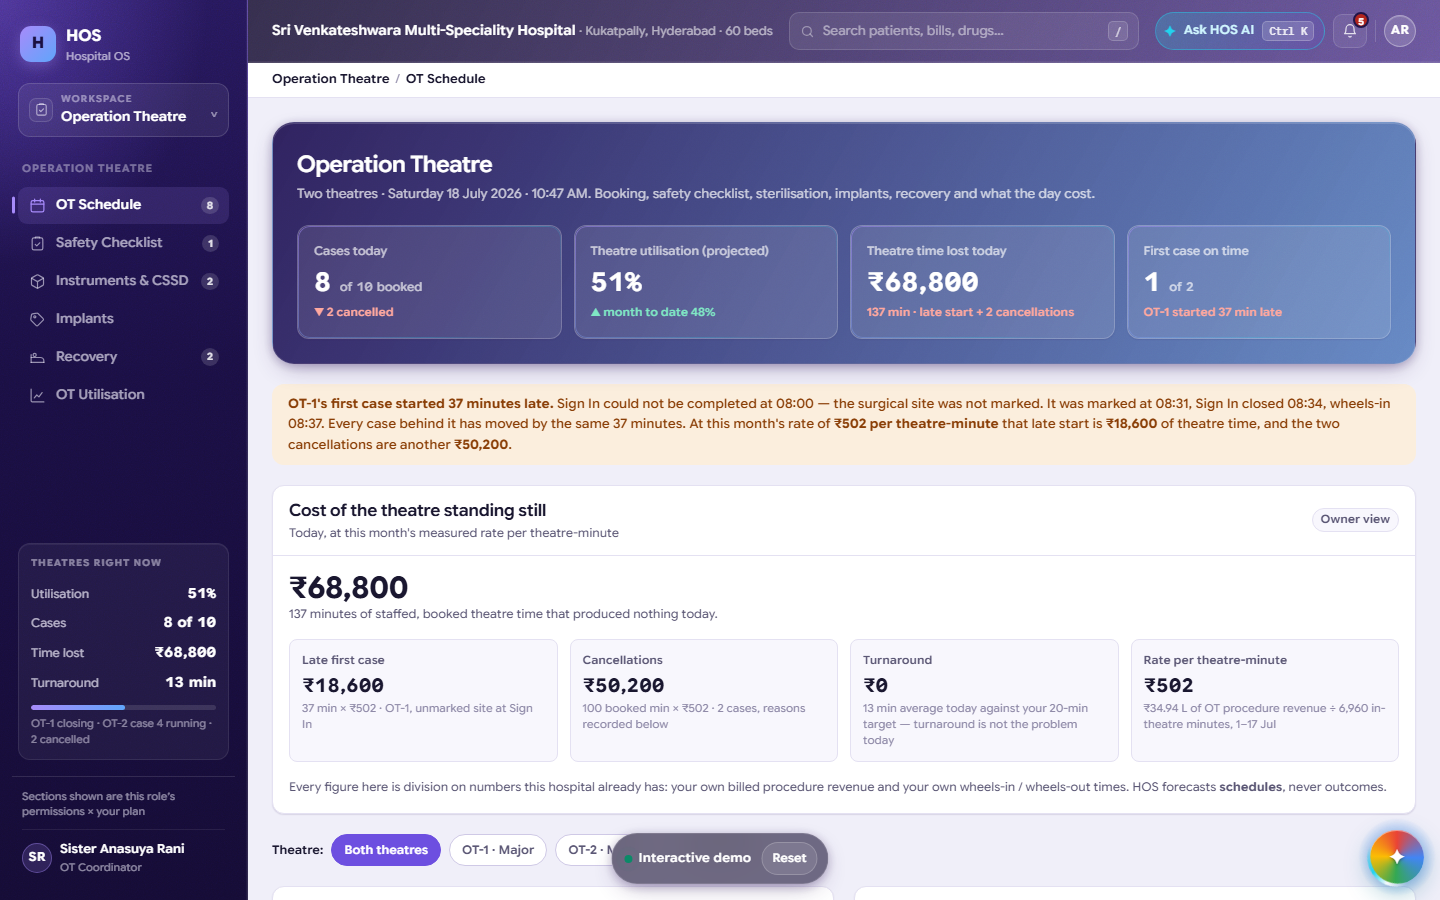
Operation theatre schedule with cost-of-idle-theatre KPIs.
14
Operation Theatre
Theatre scheduling with the cost of an idle theatre made visible, not buried in a report.
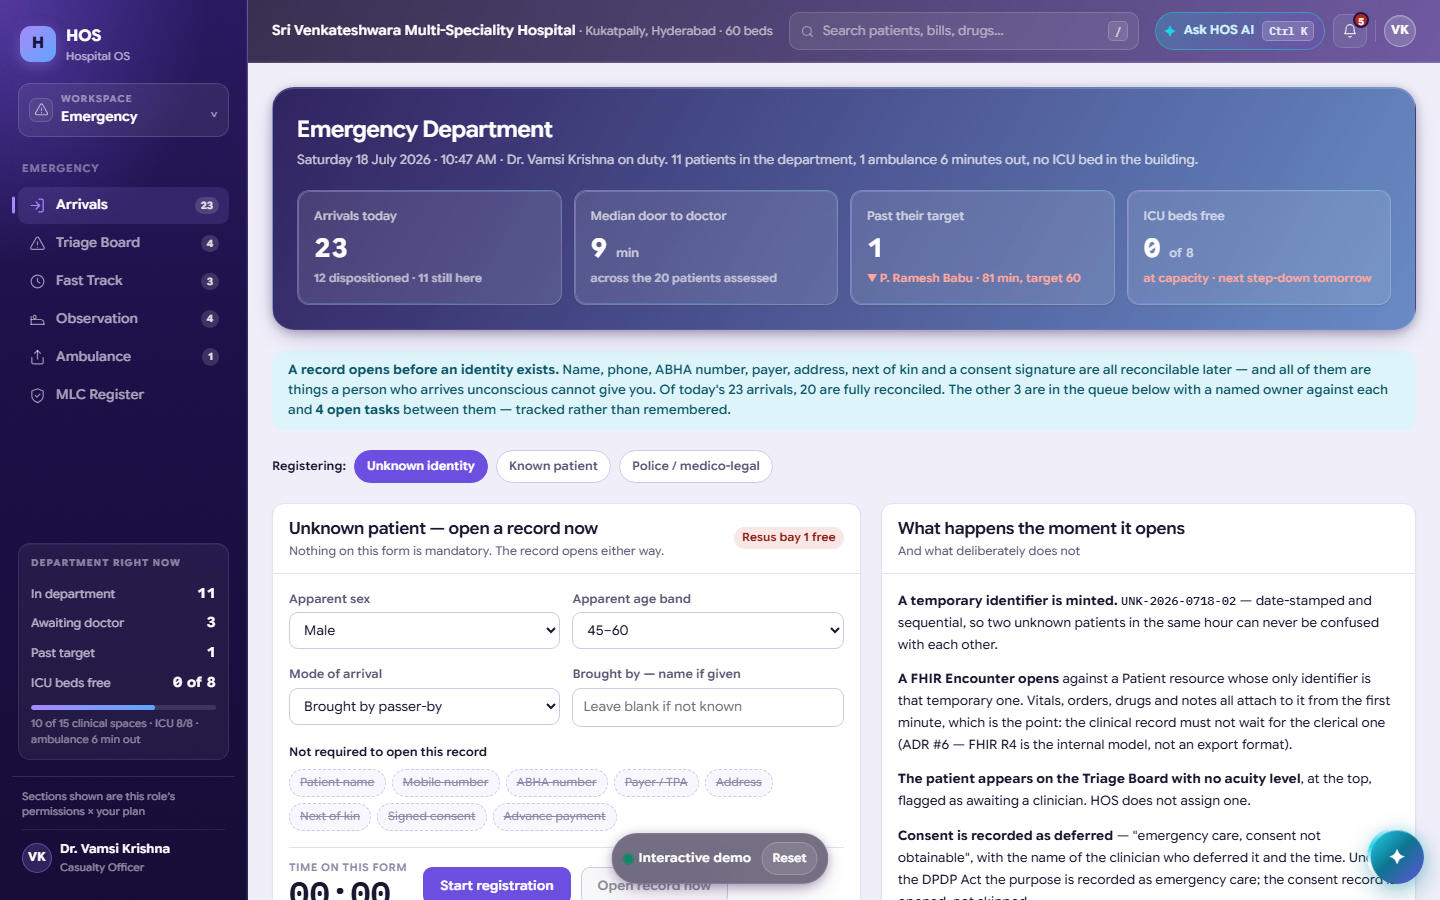
Emergency workspace with arrivals, triage board and door-to-doctor timers.
15
Emergency
A record opened for an unknown patient in seconds, arrivals and door-to-doctor timers. A clinician assigns acuity, never HOS.
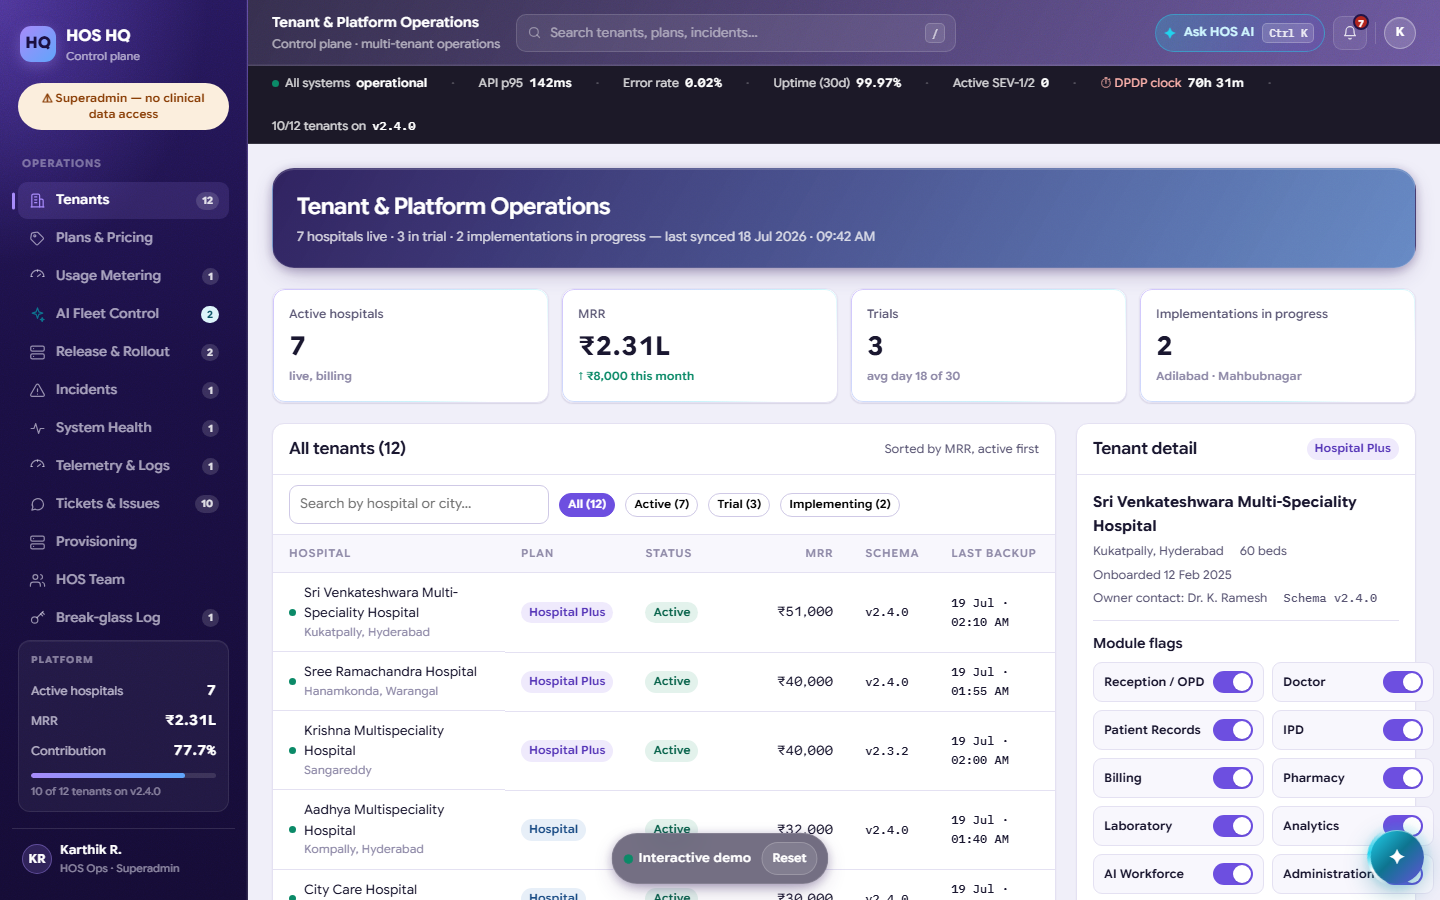
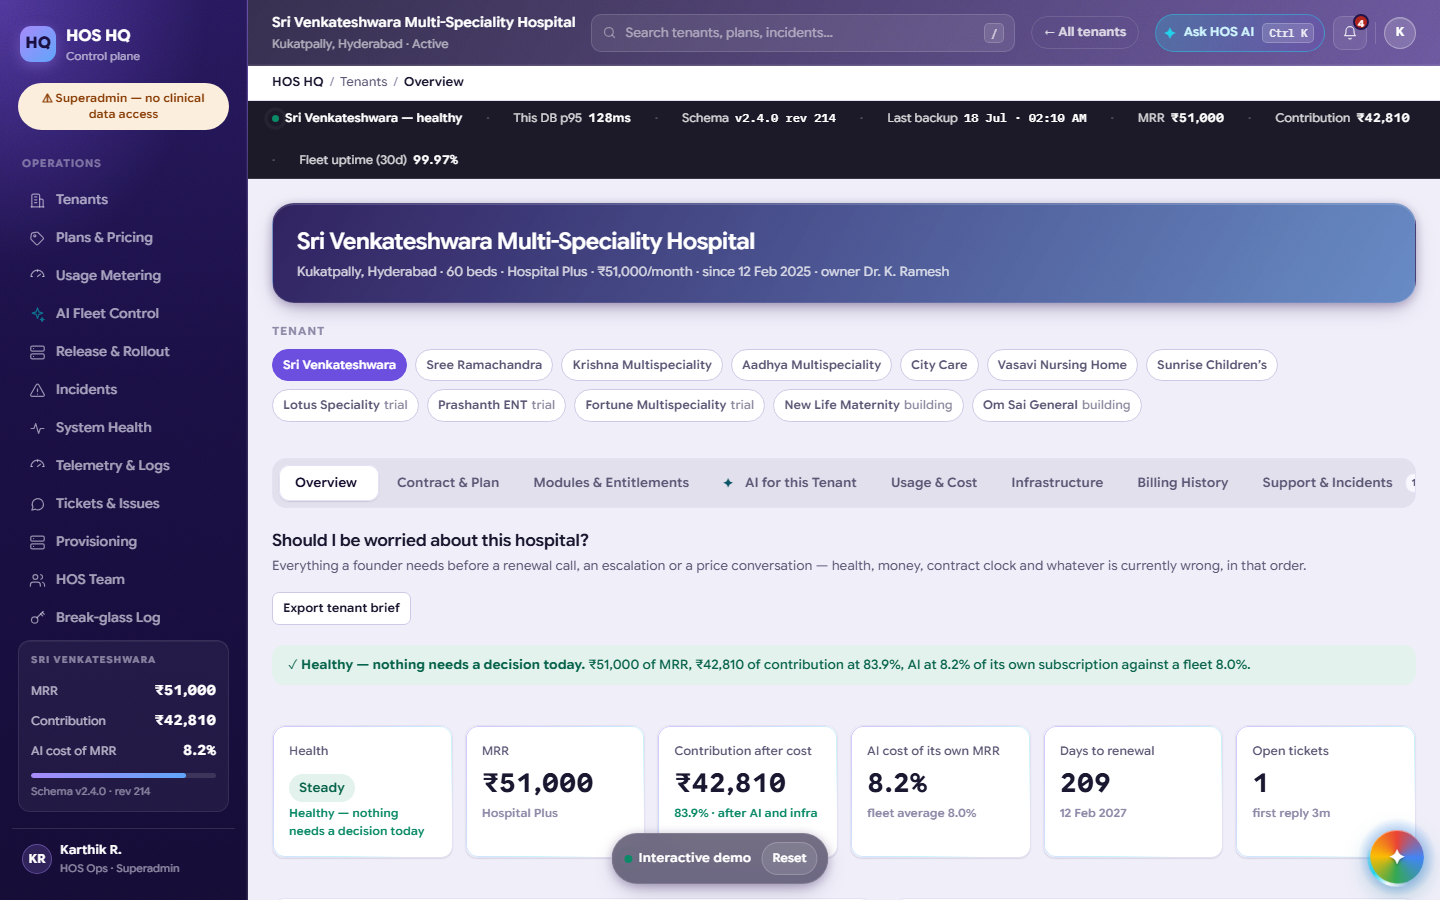
Tenant detail screen with contract, modules, AI usage, infra, billing, support and compliance tabs.
16
Tenant Detail
Full per-tenant drill-down for the platform team: contract, modules, AI usage, infra, billing, support and compliance in one screen.
The HOS patient app on a phone: B. Srinu's discharge date, his stay, and what happens next.
Not a workspace

And one app that isn't for your staff at all.

A patient signs in with a phone number and an OTP, to a different application. There is no route from it into any staff screen — that is a property of how the two are built, not a permission someone could flip.

→His results, shown against the laboratory's own ranges — the app never tells him what a value means, because that is his doctor's job
→His PM-JAY cover in plain language, and the ₹15,150 owed back to him
→Every hospital that read his records, and a revoke only he controls
→No staff notes, no unvalidated results, no other patient — structurally absent, not hidden
Open the patient app →
Built for the ground truth

Proven on a real Indian hospital first,
not a demo room.

→ABDM-native from line one. FHIR R4 is the internal data model, not a translation layer bolted on later. Scan a patient's ABHA QR and their records arrive from other hospitals — with consent, revocable any time.
→Works when the internet doesn't. Billing and dispensing keep working through a power cut; writes queue on the device with their own ids and drain when signal returns.
→Telugu, Hindi, English — and WhatsApp. The scribe handles code-switching mid-sentence, because that is how consultations actually sound.
→NABH readiness that assembles itself. Only about 2,500 of roughly 100,000 Indian hospitals are accredited, mostly because the evidence is a paper project. HOS collects it as you work.
→Your data in your own database. A dedicated Postgres database per hospital — isolation by construction. And your export is always available; we never hold patient data hostage.
→Your staff learn on synthetic patients. 40 fake patients and 18 scripted scenarios — a STAT order, an ICU deterioration, a disputed bill. Nobody learns your software on a real patient.
Pricing

Priced per hospital, not per click.

A one-time implementation of ₹50,000–₹1,00,000 covers data migration, tariff mapping and staff training on the sandbox. The ABDM Digital Health Incentive Scheme may subsidise part of it.

Hospital
₹30,000 / month
  • Up to 60 beds
  • OPD, IPD, pharmacy, lab, billing
  • AI Scribe + Billing Agent
  • Front-office agent, included — WhatsApp + AI Calling (2,000 msgs + 400 voice mins/mo)
  • ABDM M1/M2, GST invoicing
Hospital Plus most chosen
₹40,000 / month
  • Everything in Hospital
  • Theatre, casualty and nursing workspaces
  • Claims & pre-auth automation (NHCX, PM-JAY)
  • Quality & Safety + NABH tier tracking
  • AI quality dashboard and audit chain
Group
Let's talk
  • Multiple facilities, one control plane
  • Cross-facility analytics
  • Dedicated onboarding specialist
  • Custom tariff & discharge templates
Claims Recovery performance-based
% of recovery · no base fee
  • For denial appeals & underpaid-claim recovery only — not a replacement for the plans at left
  • Runs on the same Billing Agent and denial-benchmark data already in the product
  • You pay only against value actually recovered, not per seat or per message
  • Rate is quoted against your own payer mix and current denial rate — talk to us

The front-office voice agent (AI Calling) is not a separate line item — it ships as one agent with the WhatsApp assistant, because a hospital's front office is one job, not two products.

See it running before you talk to anyone.

Every screen is clickable and every number on it reconciles. Pick a role — owner, doctor, nurse, or the platform team — and walk a real shift.